

The Montessori Approach to Dementia: A Family Guide
What is the Montessori approach to dementia care? The Montessori approach to dementia care adapts the educational philosophy of Maria Montessori for people living with dementia. It focuses on purposeful, meaningful activities that build on preserved procedural memory, support independence, and draw on a person’s individual life history. Research shows it can improve engagement, reduce agitation, and support quality of life at any stage of dementia.
You’ve probably heard of Montessori in the context of schools: wooden learning materials, child-led discovery, classrooms without conventional desks. It doesn’t immediately suggest anything to do with dementia care.
That surprise is worth sitting with. Because the same principles that Maria Montessori identified at the turn of the twentieth century, learning through doing, tasks matched to the individual’s current abilities, the importance of independence, and the power of a well-designed environment, turn out to apply with striking precision to caring for someone with dementia.
If you are supporting a parent or partner with dementia at home, or trying to understand what a good care setting should look like, this guide explains the Montessori approach: where it came from, why it works, and exactly how to try it.
What Is the Montessori Approach to Dementia?
Maria Montessori was an Italian physician who developed her educational philosophy in the early 1900s. Her core insight was that people learn best through purposeful, hands-on engagement with real objects, in environments designed to support rather than hinder them, and through tasks calibrated to what they can actually do right now.
In the 1990s, American psychologist Dr Cameron J. Camp, working at the Menorah Park Center for Senior Living in Cleveland, Ohio, began adapting these principles for people living with dementia. His insight was that Montessori’s philosophy mapped directly onto what neuroscience was revealing about how dementia affects the brain.
His early work led to the development of Montessori Programming for Dementia (MPD), which he and colleagues have since tested in care homes, adult day centres, and home settings across three continents. Dr Camp has published more than 150 peer-reviewed articles and been funded by the National Institutes of Health and the Alzheimer’s Association. He is a Fellow of both the American Psychological Association and the Gerontological Society of America.
The approach has since been adopted internationally. In the UK, the Maria Montessori Institute lists Montessori for Dementia, Disability and Ageing as a programme area, and a number of UK care homes have trained staff through accredited programmes.
Why It Works: The Neuroscience of Procedural Memory
This is the part that tends to change how families think about dementia.
Dementia primarily damages declarative memory: the ability to recall names, recent events, dates, and learned facts. This is the memory that deteriorates early and visibly. It’s why your loved one may not remember what they had for breakfast, or may struggle to recall your name on a difficult day.
But there is a second memory system: procedural memory, sometimes called implicit memory. This is the memory for how to do things. How to fold a shirt. How to knead dough. How to play a chord on the piano. How to set a table. These skills were learned through years of practice and repetition, and they are stored in a different part of the brain. They are far more resilient in dementia.
Montessori-based activities target procedural memory directly. They invite a person to do something they already know how to do, rather than asking them to learn or recall anything new. The activity itself provides the structure. Memory retrieval is not required.
This is also why the approach is not condescending or childlike. The activities draw on adult skills and adult life experience. A former engineer might sort nuts and bolts. A former cook might prepare vegetables. A former seamstress might handle and fold fabric. Nothing is generic. Everything connects to who this person is.
Understanding this also helps to make sense of distressing behaviours. If you’re struggling with what looks like agitation, withdrawal, or repeated questions, our guide to what dementia behaviours are really communicating explains why so many of these responses are expressions of an unmet need, including the need for purpose.
The Six Core Principles Applied at Home
Camp’s framework rests on six principles that distinguish the Montessori approach from a standard activities programme:
- Start at the simplest level. Every task is broken into small, sequential steps. Complexity is added only when success is established.
- Use real objects and visual cues. Everyday items, physical demonstrations, labels, and templates replace verbal instruction. If someone can see what to do, they do not have to remember it.
- Anchor activities in personal history. A former teacher gets a task that connects to teaching. A former gardener gets gardening. Generic programmes designed for a group are replaced by something designed for this specific person.
- Support independence. The carer’s role is to set up the activity and step back. The goal is purposeful doing, not watching someone else do.
- Measure engagement, not the end result. Whether the laundry is folded neatly is not the point. Whether the person is actively, meaningfully occupied is.
- Enable contribution. People with dementia can sort materials for a project, care for a plant, or show a grandchild something they know how to do. Contribution, not just participation, is what creates a sense of purpose.
Montessori Activities You Can Try at Home
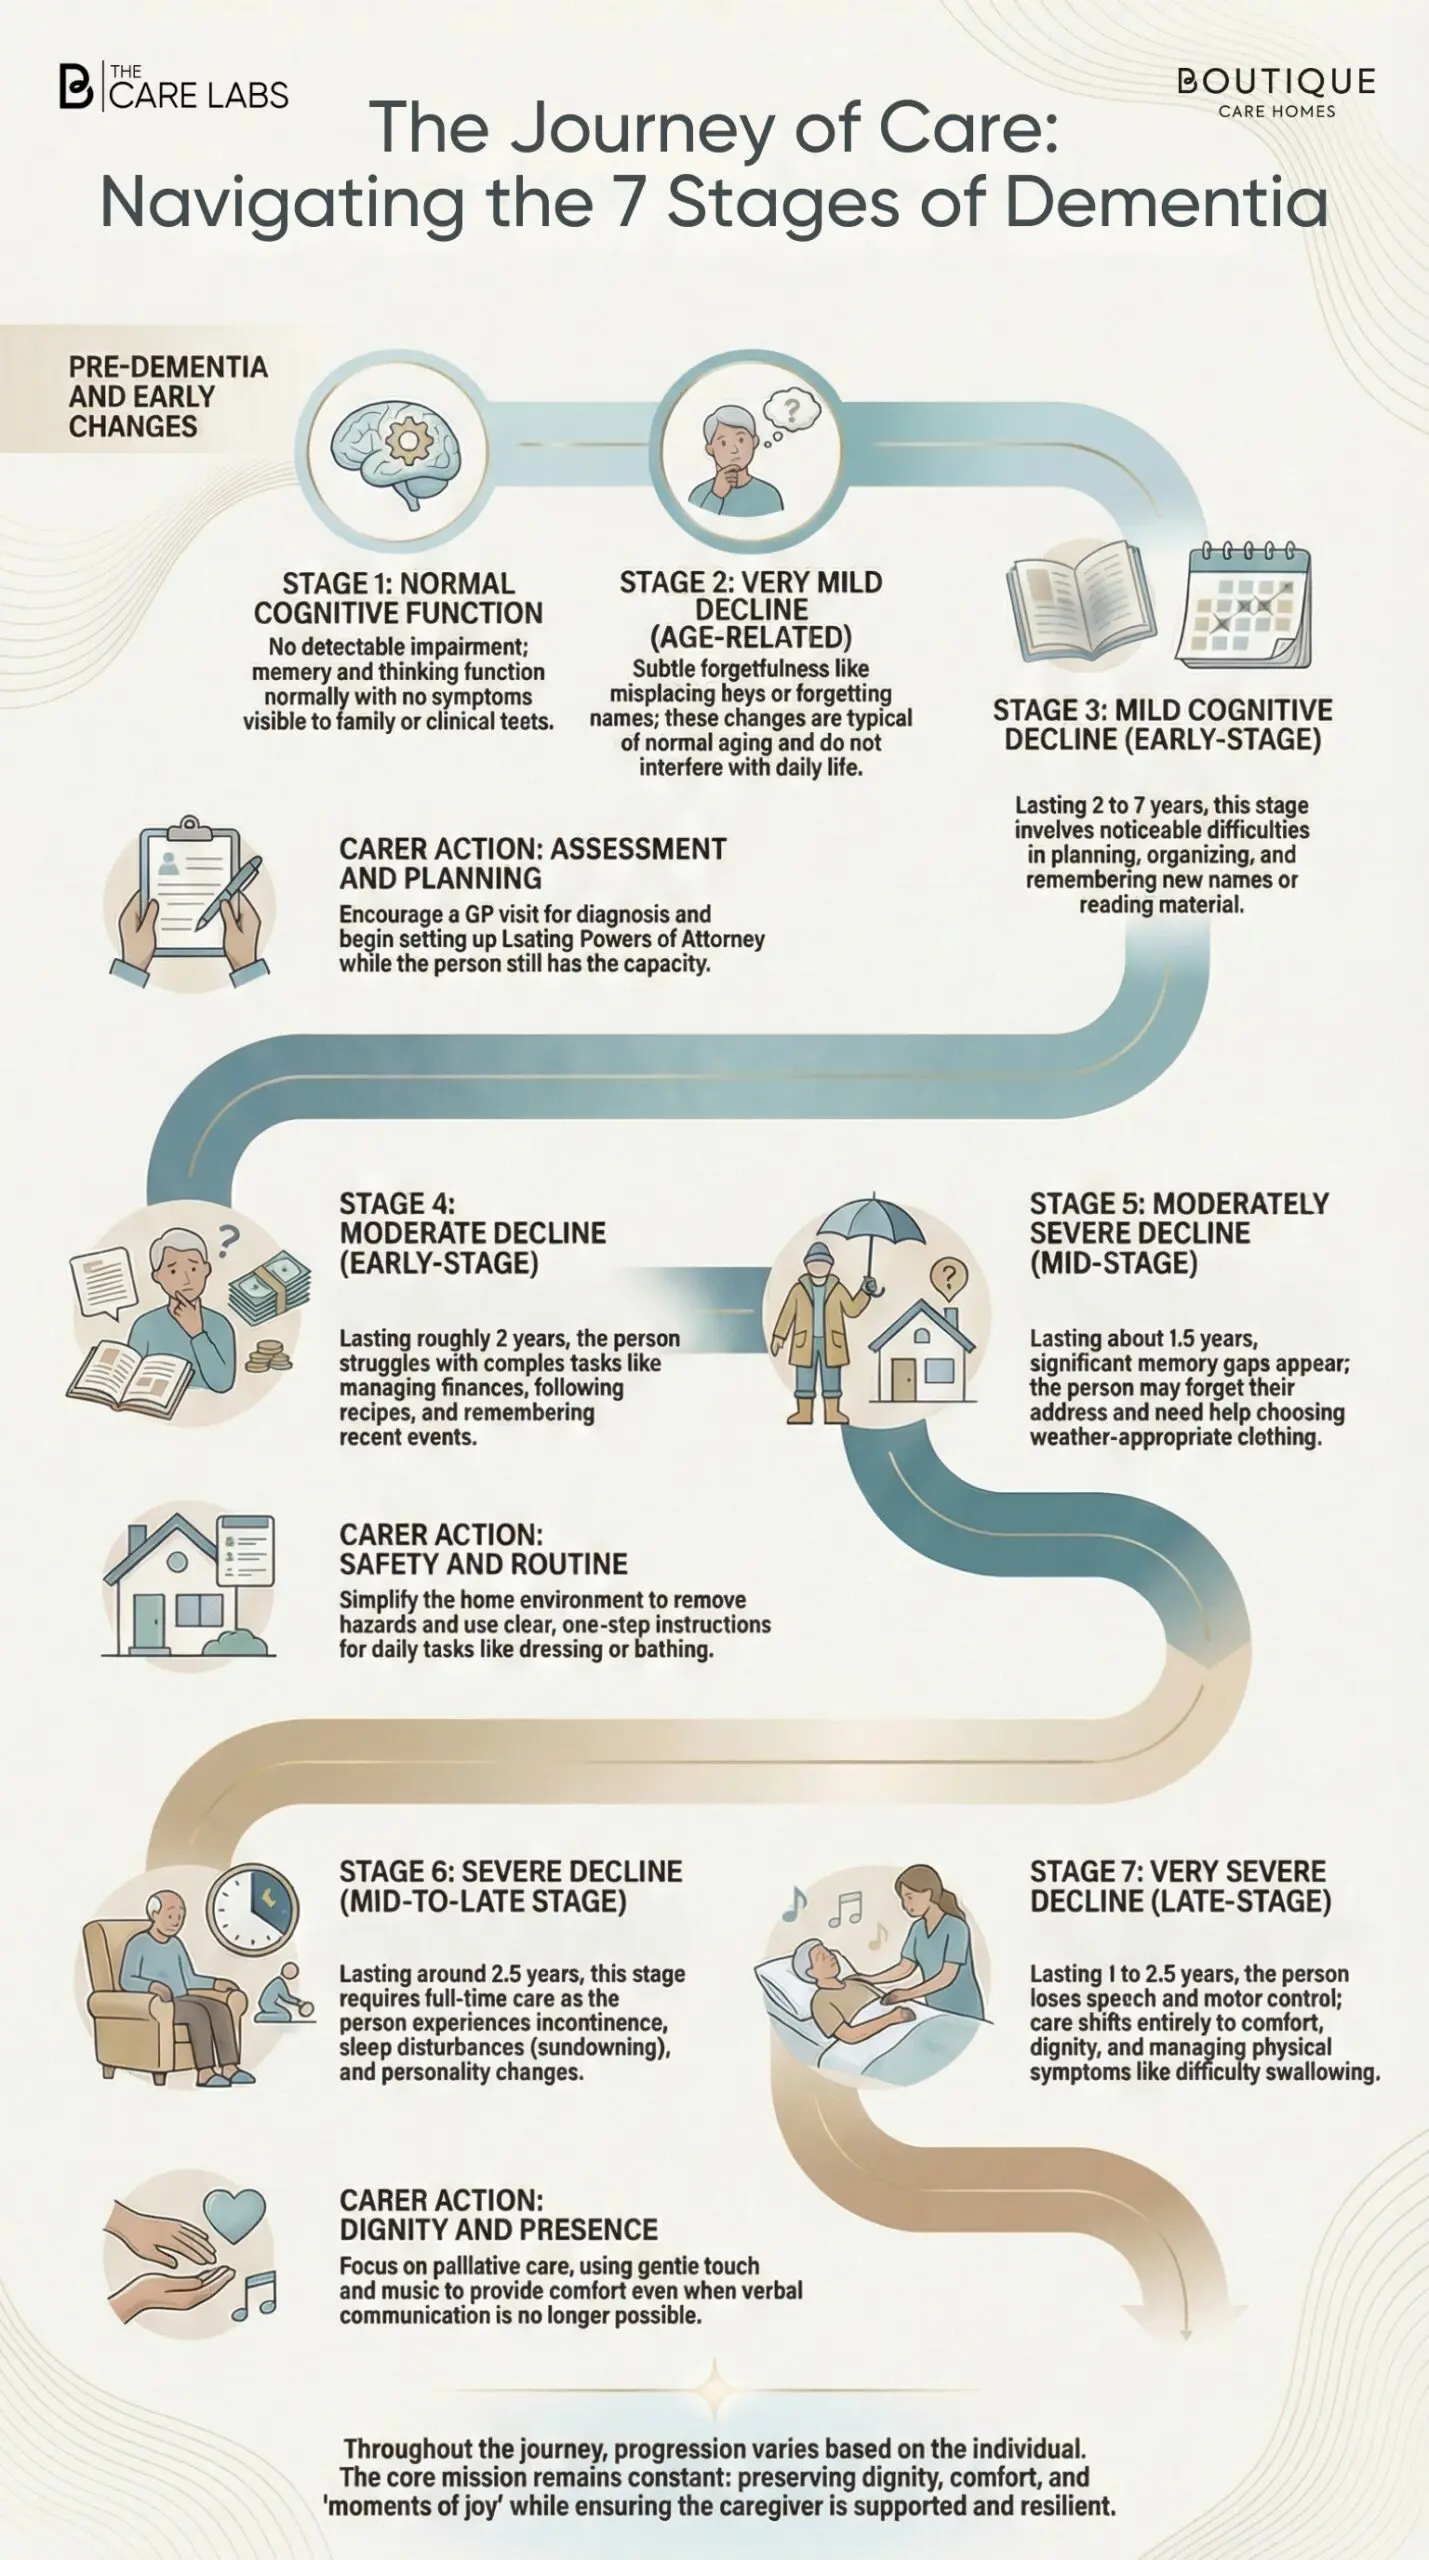
The following ideas are organised roughly by dementia stage. If you’re unsure which stage applies to your loved one, our overview of the seven stages of dementia gives a clear, practical guide.
Early Stage: Building on Existing Skills
At this stage, the person can still manage multi-step tasks but may be losing confidence. Activities should feel purposeful and meaningful, not like a test.
- Familiar cooking: Following a handwritten recipe for a dish they have made dozens of times. Keep the recipe visible. Let them lead.
- Gardening: Watering plants, planting seeds, deadheading flowers. Real tasks with visible results.
- Sorting and organising: Arranging photographs by decade, sorting cutlery, organising a collection of objects by colour or size. These engage procedural memory without requiring recall.
- Life story work: Gathering photographs and mementos into a personal album. This also creates a resource you can return to together at any stage.
Moderate Stage: Simplifying Without Removing Meaning
Tasks need to be broken into fewer steps. The environment matters more: reduce clutter, reduce background noise, reduce competing demands.
- Laundry folding: Shirts, towels, facecloths. One type at a time, on a clear surface.
- Simple food preparation: Stirring, peeling soft vegetables, buttering bread, measuring ingredients.
- Sensory activities: Handling objects with distinct textures (wool, smooth stone, polished wood), smelling familiar herbs or flowers, arranging objects in a particular order.
- Music and reminiscence: Listening to music from their young adult years, singing along, or keeping time. Music therapy is one of the most robust non-pharmacological approaches for dementia, and it sits naturally within a Montessori framework of meaningful, sensory engagement.
- Intergenerational tasks: When children visit, structured tasks work well: reading a short story aloud together, or showing a grandchild something the person knows how to do. Dr Camp developed a programme called Resident-Assisted Montessori Programming (RAMP) in which people with early-to-moderate dementia successfully led group activities for those at a later stage. The capacity to teach, to guide, persists further than most families expect.
Later Stage: Sensory Engagement and Presence
A common and painful misconception is that nothing can reach someone in the later stages of dementia. Research says otherwise.
A study by Orsulic-Jeras, Judge, and Camp, published in The Gerontologist (2000), found that residents with advanced dementia showed significantly more constructive engagement and significantly more pleasure during Montessori-based activities than during standard activities programmes. The NHS dementia activities page, last reviewed in September 2024, states directly: “It’s often assumed that people in the later stages of dementia are unable to engage in activities, but this isn’t true.”
At this stage, activities focus on sensory experience, presence, and simple physical action:
- Familiar objects with strong personal associations: A well-worn tool, a piece of jewellery, a length of fabric from an old garment.
- Sensory engagement: Hand massage with a familiar scent, handling smooth objects, listening to a familiar voice recording or piece of music.
- Single-step physical tasks: Placing smooth stones into a bowl, folding a piece of cloth, turning pages of a familiar book.
Our complete guide to dementia activities at home has further ideas across all stages.
Setting Up a Montessori-Friendly Home Environment
The Montessori concept of the “prepared environment” applies as much in a living room as in a care facility. You don’t need specialist equipment.
- Reduce clutter from the activity space. A clear surface signals: this is where we work. Too many objects are distracting and confusing.
- Use visual labels. Simple labels on cupboards, drawers, and containers, with pictures where helpful, allow independent navigation without having to ask or remember.
- Keep activity materials visible and within reach. A basket of familiar objects in plain sight is far more likely to be engaged with than materials stored away in a drawer.
- Reduce background noise during activity time. Television and radio off. One source of sensory input at a time.
- Choose real objects over replicas. A real wooden spoon rather than a toy one. Familiar, everyday objects engage procedural memory more reliably.
- Build a consistent routine. An activity at the same time each day, perhaps mid-morning when energy tends to be higher, creates a predictable rhythm that supports engagement.
For broader guidance on adapting the home, our guide to creating a dementia-friendly home environment covers layout, lighting, safety, and sensory design.
What the Evidence Shows
The research base for Montessori-based dementia care has grown steadily since Camp’s first publications in the late 1990s. Here is what peer-reviewed research shows, with sources cited honestly:
Engagement and affect: Judge, Camp, and Orsulic-Jeras (2000), published in the American Journal of Alzheimer’s Disease, found that people with dementia in Montessori-based programmes showed significantly more constructive engagement, direct verbal or physical interaction with the activity, and significantly less passive engagement than those in standard activities.
Agitation and quality of life: A 2013 randomised trial by Van der Ploeg, Eppingstall, Camp, and colleagues, published in International Psychogeriatrics, found that personalised, one-to-one Montessori-based activities led to measurable improvements in agitation, positive affect, and engagement in nursing home residents with dementia.
Broader clinical outcomes: A 2023 systematic review indexed on PubMed Central (PMC10336713) concluded that Montessori-based programmes show positive effects across a range of outcomes: feeding difficulty, engagement, affect, cognition, verbal communication, quality of life, and family relationships. The review also found evidence of reduced agitation and, in some settings, reduced use of psychotropic medication.
An honest caveat: Most studies in this area are conducted in the United States, Australia, and Taiwan, and many involve small sample sizes. No UK-specific randomised controlled trials of the Montessori approach to dementia were identified at the time of writing. The evidence is consistent and encouraging. It points to real potential rather than certainty, and it is strong enough to justify trying these approaches at home.
Working with a Care Team
If your loved one attends a day centre or lives in a residential care setting, you can ask directly whether Montessori-based approaches are part of their programme. Useful questions include:
- Is the activity programme tailored to each person’s life history and individual interests?
- How do staff identify what is meaningful for a particular resident, not just for the group?
- What non-pharmacological approaches are used to support people who become distressed?
If you are caring for someone at home, you do not have to design activities alone. Our guide to caring for someone with dementia at home covers the practical and emotional challenges of the caring role.
Frequently Asked Questions
What is the Montessori approach to dementia care?
The Montessori approach adapts the educational philosophy of Maria Montessori for people living with dementia. Developed by American psychologist Dr Cameron Camp in the 1990s, it focuses on purposeful, meaningful activities that draw on preserved procedural memory, use real objects and visual cues rather than verbal instruction, and connect to the person’s individual history and skills. It is used in care homes and home settings across the UK and internationally.
Isn’t Montessori just for children?
This is the most common question, and it is a reasonable one. Montessori’s original insight was about how all human beings learn: through doing, through real objects, through tasks matched to their current abilities. Dr Camp saw that these principles applied directly to people with dementia. The activities used are not childish. They draw on adult skills and adult life experience. A former cook handles kitchen equipment. A former teacher sorts and organises materials. The person’s history is the starting point, not a children’s curriculum.
Does it work for someone in the later stages of dementia?
Yes. Research by Orsulic-Jeras, Judge, and Camp (2000), published in The Gerontologist, found that people with advanced dementia showed significantly more engagement and pleasure during Montessori-based activities than during standard activities programmes. The NHS states explicitly that assuming people in later-stage dementia cannot engage is not accurate. At this stage, activities are simpler and more sensory in nature, but engagement remains possible and meaningful.
How is this different from regular activities in a care setting?
Standard group activities are designed for participation and are often the same for everyone. The Montessori approach is individualised: activities are chosen based on this person’s specific skills, history, and interests. It also prioritises independence (the person does the task; the carer sets it up and steps back), meaningful contribution rather than entertainment, and the use of familiar real objects and visual cues rather than verbal instruction or group prompts.
Can I do this at home without professional training?
Yes. Dr Camp explicitly trained family members, daughters, and home carers to use Montessori-based techniques. No certification is needed to start. The core principles are straightforward: break tasks into small steps, use real and familiar objects, build on what the person already knows how to do, and allow them to lead. Start with one familiar activity. Observe what works and what doesn’t. Adjust.
What should I do if my loved one refuses to take part?
Refusal usually means one of three things: the task is too hard, it isn’t personally meaningful, or it is being introduced in a way that feels pressured. Try a simpler version of the same activity. Introduce it without framing it as an activity: sit alongside them and start doing it yourself. If refusal is accompanied by distress or agitation, our guide to what dementia behaviours are really communicating may help you understand what is driving it.
Can it help with agitation or repetitive behaviour?
Research suggests it can. The 2013 randomised crossover trial by Van der Ploeg and colleagues (International Psychogeriatrics) found measurable reductions in agitation when people with dementia received personalised Montessori-based activities. A 2023 systematic review (PMC10336713) found evidence of reduced agitation and, in some settings, reduced psychotropic medication use. Agitation is often a response to boredom, frustration, or an unmet need for purpose. Meaningful, purposeful activity directly addresses that need.
Where can I find further support?
Dementia UK offers specialist Admiral Nurse support and can be reached by phone or online. The Alzheimer’s Society has a helpline, local groups, and practical guidance for families at every stage. The NHS dementia activities page includes suggestions for activities across dementia stages. For a library of plain-English guides covering the full care journey, visit The Care Labs at thecarelabs.co.uk.
What This Approach Is Really About
The Montessori approach is sometimes described as a method, a framework, or a programme. At its simplest, it is a shift in perspective.
It asks: what can this person still do, rather than what have they lost? What matters to them, rather than what is easy for us? How do we set up the environment so they can succeed, rather than waiting for them to struggle?
That shift is available to every family. You do not need specialist equipment, formal training, or a purpose-built facility to start. You need a familiar task, a clear surface, and the willingness to step back and let someone who has done this a thousand times do it again.
Sources
- Camp, C.J. (2010). Origins of Montessori Programming for Dementia. Nonpharmacological Therapies in Dementia, 1(2), 163–174. https://pmc.ncbi.nlm.nih.gov/articles/PMC3600589/
- Judge, K.S., Camp, C.J., & Orsulic-Jeras, S. (2000). Use of Montessori-based activities for clients with dementia in adult day care: Effects on engagement. American Journal of Alzheimer’s Disease, 15, 42–46. (Cited in Camp, 2010, above)
- Orsulic-Jeras, S., Judge, K.S., & Camp, C.J. (2000). Montessori-based activities for long-term care residents with advanced dementia: Effects on engagement and affect. The Gerontologist, 40, 107–111. https://doi.org/10.1093/geront/40.1.107
- Van der Ploeg, E.S., Eppingstall, B., Camp, C.J., Runci, S.J., Taffe, J., & O’Connor, D.W. (2013). A randomized crossover trial to study the effect of personalized, one-to-one interaction using Montessori-based activities on agitation, affect and engagement in nursing home residents with dementia. International Psychogeriatrics, 25, 565–575. Referenced at https://amshq.org/blog/dementia/the-montessori-method-applied-to-dementia
- The impact of Montessori-based programmes on individuals with dementia living in residential aged care: A systematic review. (2023). PMC10336713. https://pmc.ncbi.nlm.nih.gov/articles/PMC10336713/
- NHS. (2024). Activities for dementia. Last reviewed 19 September 2024. https://www.nhs.uk/conditions/dementia/living-with-dementia/activities
- Dementia UK. Meaningful activities for a person with dementia. https://www.dementiauk.org/news/meaningful-activities-for-a-person-with-dementia
- Alzheimer’s Society. https://www.alzheimers.org.uk
- Maria Montessori Institute (UK). Montessori for Dementia, Disability and Ageing programme area. https://mariamontessori.org
Other articles that you may like


The Moment I Knew: Finding Dementia Care for Mum
 Read More